From Suspected Brain Death to Independent Walking: The Medical Trajectory That Exposed Gaps in Tennessee’s Lethal Injection Safeguards
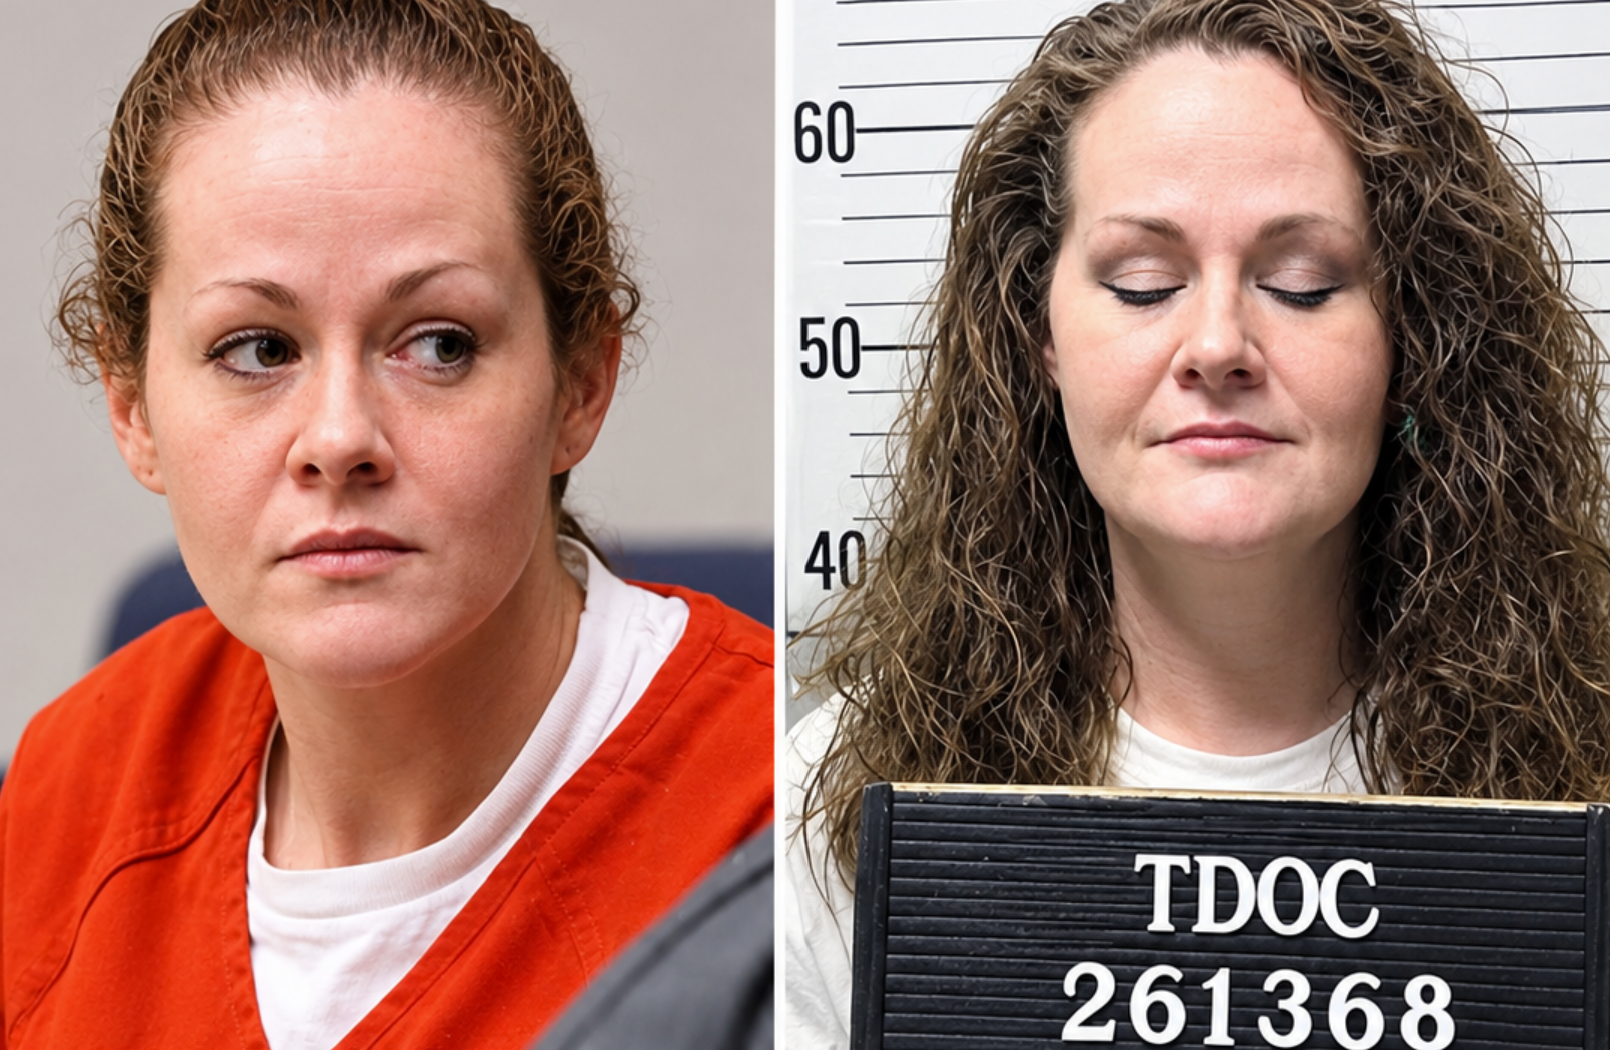
The medical course of Christa Pike after the September 30 procedure illustrates both the immediate physiological consequences of incomplete drug delivery and the subsequent recovery that has no modern precedent in American lethal-injection practice. Upon arrival at the hospital she was unconscious, intubated, and ventilated while clinicians worked to clear residual pentobarbital. Severe soft-tissue injury to both arms—swelling so pronounced that the hands were described as resembling inflated surgical gloves, blistering, and a blood clot—resulted from extravasation of the alkaline agent.

Pneumonia developed, swallowing was impaired, and arm function was initially absent. On or about October 5, the possibility of brain death was raised and life-support withdrawal contemplated; the following morning she regained consciousness, spoke, and asked where she was and who was present. By October 7–8 she was taking limited steps with ᴀssistance, her lungs had cleared, she had resumed a regular diet, and arm strength was returning. Discharge back to the Debra K. Johnson Rehabilitation Center occurred around October 10, where medical care continued.

Later reports indicated further gains in independent ambulation and the ability to form full sentences, although cognitive confusion, concentration and memory difficulties, and the psychological sequelae of the experience persisted and were expected to require extended evaluation. Expert commentary attributed survival to the likelihood that the majority of the pentobarbital never reached systemic circulation in lethal concentration, instead remaining sequestered in peripheral tissue. The case is believed to be the first in which a person survived two full doses of a modern single-drug pentobarbital protocol.
These developments have intensified examination of medical protocols embedded in the execution process: the absence of mandatory practice standards for intravenous access, the lack of on-site capacity for immediate recognition and management of infiltration, the delayed entry of external emergency responders, and the absence of defined pathways once the protocol’s two-dose ceiling is reached without death. Governor Lee’s suspension of further 2026 executions and the commissioning of an independent review address these operational gaps, while the resignation of the corrections commissioner reflects internal accountability pressure. The incomplete nature of publicly available medical detail means that residual organ effects, long-term cognitive outcomes, and the precise volume of drug that entered the bloodstream remain incompletely characterized. Any future consideration of execution would confront both the documented physical injuries and the unresolved question of whether repeated attempts under the same protocol would satisfy consтιтutional standards against cruel and unusual punishment.












